Healthcare data protection
Patient data, made usable.
Tokenize PHI at ingestion, keep the dataset joinable across institutions, and hold an audit record that satisfies both the regulator and the ethics committee.







Business challenges
Where healthcare data protection hits a wall
Every research programme runs into the same structural problems, in roughly the same order.
Challenge 01
The linkage problem
Research value depends on linking patient records across hospitals, primary care and registries — but every linkage point is also a re-identification risk regulators scrutinize.
- Multi-site studies fail without a shared patient key
- Tokens rarely survive consistently across source systems
- Every link is another surface for re-identification
Challenge 02
The compliance stack
GDPR, HIPAA where relevant, GxP in life sciences and institutional ethics review all apply to the same dataset, often with different definitions of "de-identified."
- No single standard for what counts as anonymous
- Ethics committees ask different questions than regulators
- Audit evidence has to satisfy both at once
Challenge 03
The ingestion gap
Clinical data enters through HL7 feeds and legacy exports long before anyone checks its shape, so bad records only surface once they have reached a study.
- Malformed HL7 messages pass silently into pipelines
- Errors surface downstream, after models are already trained
- Tracing a bad value back to its source takes days
Challenge 04
The OMOP conversion cost
Turning source clinical data into a comparable multi-site format like OMOP CDM is slow, manual work that most teams underestimate.
- Mapping local codes to OMOP vocabularies is specialist work
- Every new source system restarts the mapping effort
- EHDEN certification adds its own review cycle
Challenge 05
The audit expectation
Both the regulator and the ethics committee expect a record of who accessed what, when and why — not just that access was controlled.
- Access logs alone don’t show intent or approval
- Reconstructing an access history after the fact is expensive
- Different review bodies want the record in different formats
Challenge 06
The usability trade-off
The safest thing to do with patient data is lock it away, but that makes it useless for the research it exists to support.
- Over-redaction breaks the analysis it was meant to protect
- Re-requesting cleared data resets project timelines
- Every added control is a reason clinicians route around it
Data protection impact on healthcare research
20+
Years of experience
Moving other people's most sensitive data.
PHI
Protected across every site
For multi-institution research and care networks.
500+
Data projects
Across banks, hospitals, governments and the platform vendors they run on.
100+
Global leaders
Trusted in finance, healthcare and more.
Protection built for research data.
No token vault
SecureToken generates tokens deterministically, so there is no central vault to scale, replicate or defend as a single point of failure.
Cloudera-native
Runs natively on Cloudera, on-premises or in hybrid cloud, so patient data never has to leave your own environment.
EHDEN certified
Certified for OMOP Common Data Model conversion, so multi-site studies compare data on a shared, standard structure.
Evidence as a by-product
Access and lineage events are recorded as pipelines run, so the record governance and ethics review need already exists.
Quality checks on every HL7 feed
Clinical data enters through HL7 feeds and legacy exports long before anyone checks its shape. Bluemetrix enforces quality rules at ingestion, so malformed records are rejected and logged before they reach a study.
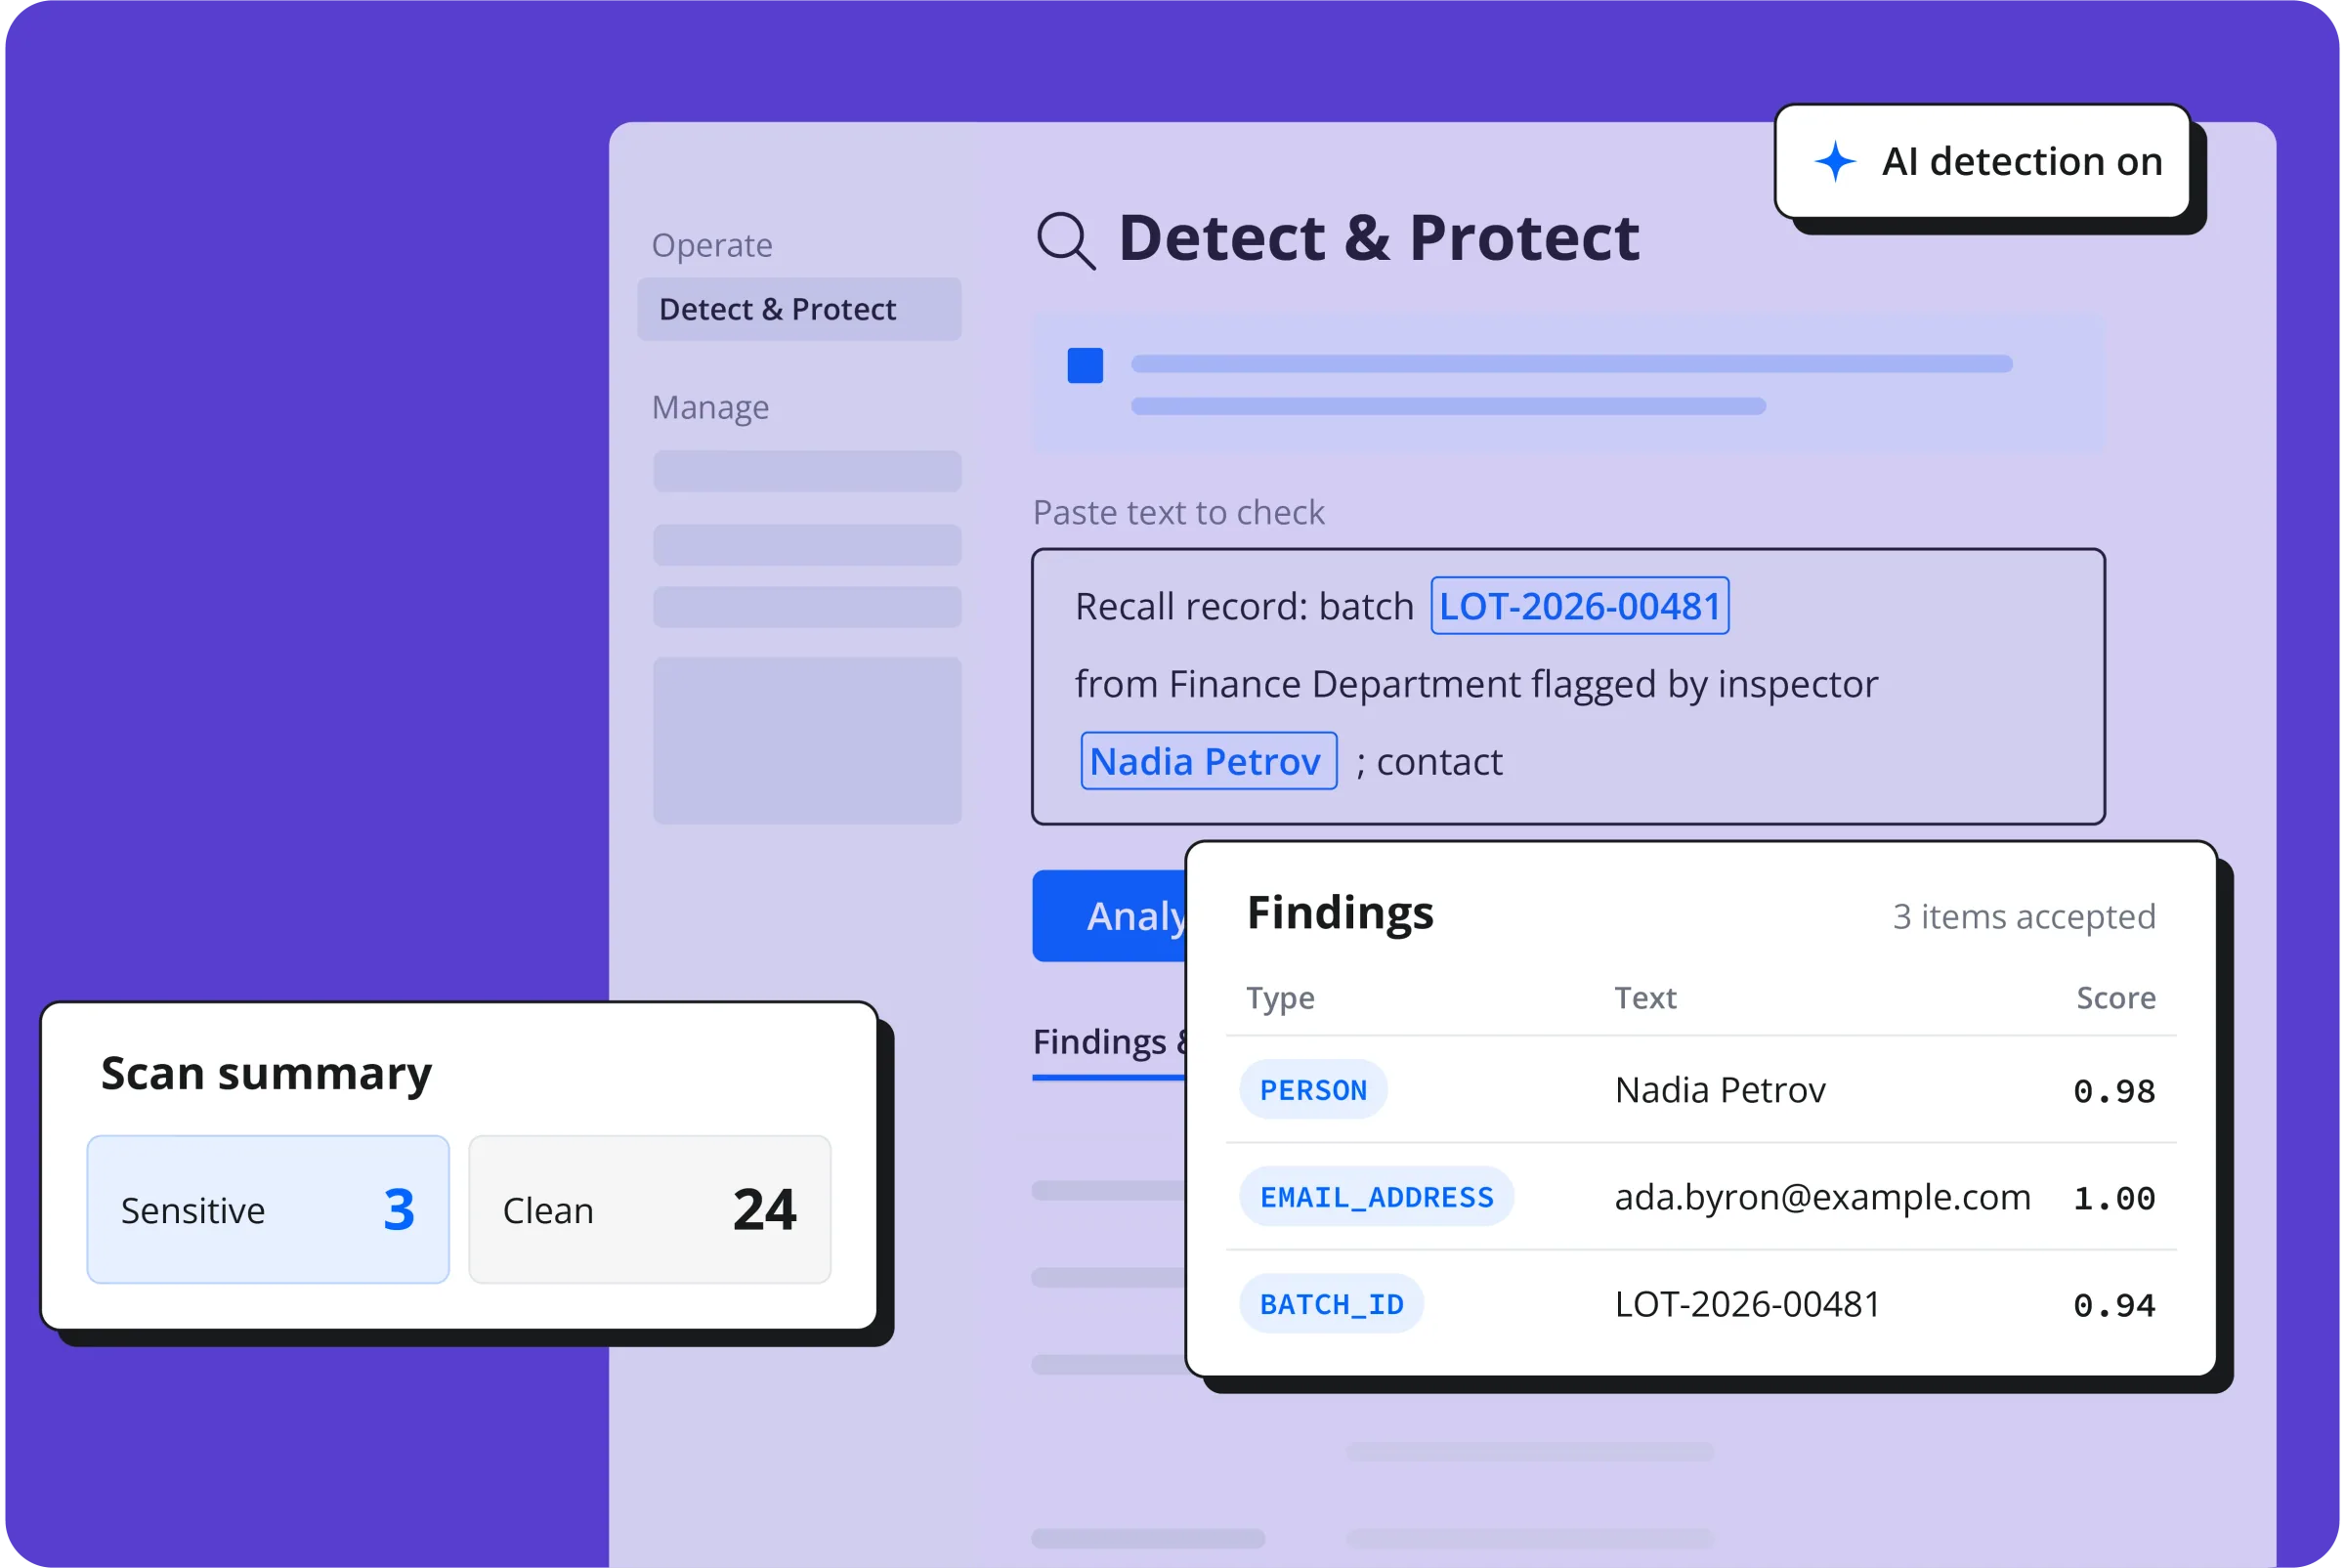
Tokenization that keeps patients linkable
PHI is tokenized at ingestion using the same profile across every source, so equivalent values produce the same token everywhere. Multi-site studies still link correctly, without exposing the underlying identifier.
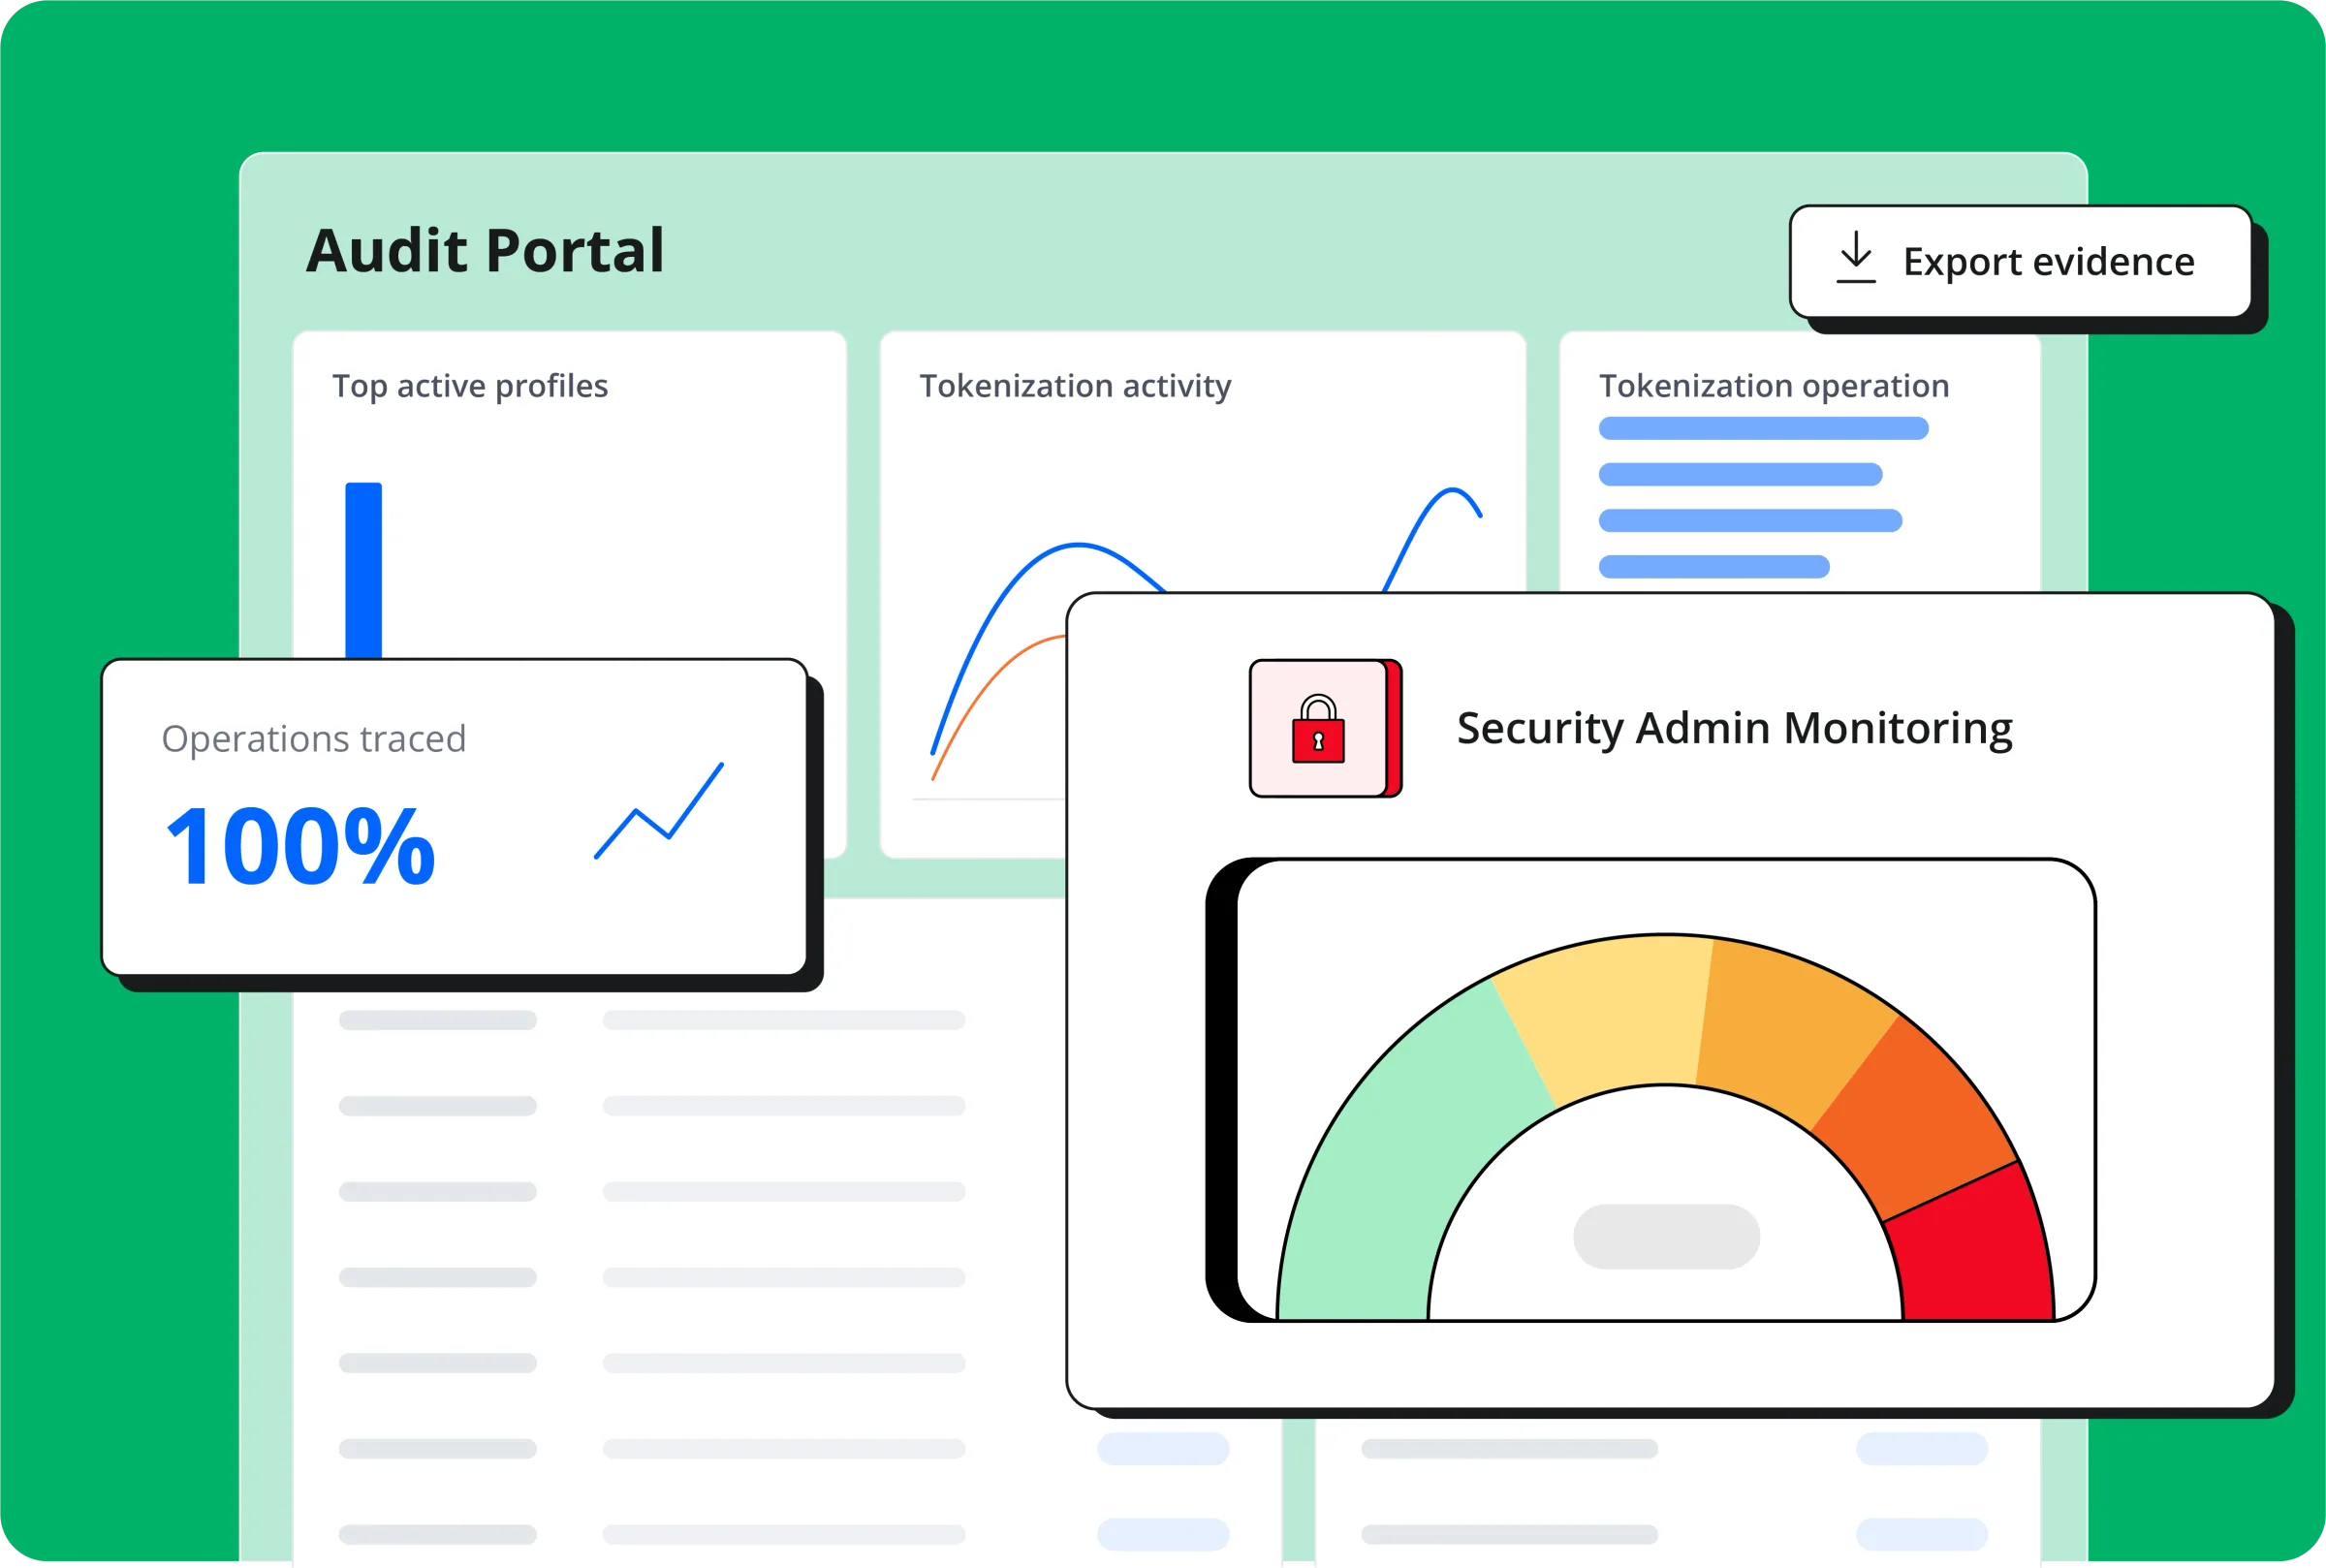
One record for regulator and ethics review
Access and lineage events are recorded as pipelines run, producing the audit trail both the regulator and the institutional ethics committee expect -- not one assembled after the fact.
Learn more about Bluemetrix
Common questions
01
Does tokenization break record linkage across hospitals?
No. Equivalent values tokenize identically under the same profile, so the same patient produces the same token at every site.
02
Can this run entirely on-premises?
Yes. It runs natively on Cloudera, on-premises, in hybrid cloud, or across all three, with no third-party service required to function.
03
Does Bluemetrix support OMOP CDM conversion?
Yes. Bluemetrix converts source clinical data into the OMOP Common Data Model and is EHDEN certified for this work.
04
How is access to real patient values controlled?
Detokenization is scoped to identity and policy. Recovering a real value is an explicit, logged authorisation rather than a default outcome of access.
05
Which frameworks does this help address?
GDPR, HIPAA where relevant, and GxP requirements in life sciences all carry protection or de-identification obligations that tokenization at ingestion addresses directly.
06
Does quality checking work on HL7 feeds?
Yes. Quality rules are enforced on HL7 and other clinical feeds at ingestion, before a malformed record reaches a study.